thiamine deficiency - Page 2

Diet Induced Pseudo-Hypoxia and Hypertension

15.2K views

Although hypertension has become almost exclusively used to indicate high blood pressure, it is worth examining the true underlying meaning. The prefix “hyper” is from the Greek, meaning over or above. Tension is defined as “the state of being stretched tight”. Perhaps then it is worth looking at how this applies to blood pressure.

When a blood pressure is measured, there are always two figures represented. The higher number is known as “systolic” and the lower one as “diastolic”. The systolic is when the heart is contracting and indicates the ability of the arterial system to expand enough to accommodate the pressure from an increased volume of blood. The diastolic indicates the pressure in the arterial system when the heart is resting between beats. We are therefore looking at the highest and lowest pressures in a closed tube system that must be capable of expanding and contracting.

Since the system is made from live cells, it does not behave like a rubber tube with elastic recoil. The arteries where blood pressure is measured are lined with muscles. It is the contraction and relaxation of these muscles that control the capacity of the artery to accommodate the amount of blood arriving from the heart. The muscles are controlled by nerves carrying messages from the brain. These muscles are completely different from those that are activated willingly, such as those in the limbs. They are contracted and relaxed automatically by a part of the brain that acts more like a computer. The body muscles are activated by a nervous system known as “voluntary”. The arterial muscles are activated by a completely separate an involuntary nervous system known as autonomic (ANS). We therefore have to examine the control mechanisms.

Understanding the Autonomic Nervous System

I have discussed this nervous system many times in Hormones Matter because, when it goes wrong, it is a potent source of disease. The nerves of this system go to every organ within the body. The control system is in the lower part of the brain. It consists of two channels. One is known as sympathetic: the other is known as parasympathetic. Although they work together, their actions oppose each other and I will try briefly to outline this dichotomy.

Sympathetic. The sympathetic nervous system is designed for both physical and mental action through a reflex mechanism known as the fight-or-flight. It prepares us to meet an enemy or escape from danger. One of its actions is to raise the blood pressure. It does this by contracting the arterial muscles already described.

Parasympathetic. When the action is completed, the brain controls automatically withdraw the activity of the sympathetic and initiate those of the parasympathetic nervous system. When this happens, the body is prepared for resting.

Chronic Activation of the Sympathetic Nervous System

There is a large amount of evidence in the medical literature that this is the primary cause of chronically high blood pressure. If the system is healthy, the blood pressure will go down on completion of the action. If not, the blood pressure remains elevated. From here, I am going to hypothesize why this happens. Please remember as you read it that it is a hypothesis, not a proven fact.

Hypoxia. This word simply means lack of oxygen. Obviously, this is a dangerous state for the brain and it is not surprising that it will activate the sympathetic component described above, including raising the blood pressure.

Pseudo-hypoxia. The prefix “pseudo”, meaning false, or sham (from the Greek, lying, false) has been used in the medical literature to describe a state that is exactly like that of hypoxia when the presence of oxygen is normal. In order to understand this, focus on the fact that oxygen must be introduced to the body but is completely useless unless it is consumed. Therefore we must try to indicate how oxygen consumption occurs.

Oxidation and burning. All forms of burning are derived from oxygen combining with a fuel, liberating heat energy. That is why we are warm blooded, but other forms of energy are produced to drive physical and mental function. Because the burning is incomplete, ash is formed. Our cells derive their energy by the oxygen, delivered in the blood from the lung, combining with glucose. The “ash” is carbon dioxide and water, discarded in the breath. The oxidation of glucose is governed by a set of enzymes that require the vitamin B complex for their action. The leader of this orchestration appears to be vitamin B1 (thiamine). That is why many papers have appeared in the medical literature that describes thiamine deficiency as a cause of pseudo-hypoxia. Its function is to catalyze the enzymes essential for oxidation. Its deficiency results in lack of sufficient energy. It is therefore not surprising that one of the symptoms of thiamine deficiency is fatigue.

Calorie/thiamine ratio. A healthy diet provides us with calorie producing elements that are broken down to glucose and used as fuel. The amount of thiamine provides a normal calorie/thiamine ratio that enables efficient oxidation. If we load the diet with empty calories (calories without essential non-calorie nutrients that include thiamine) the calorie/thiamine ratio becomes abnormal. Measuring the concentration of thiamine in the blood would be normal for a healthy diet but inadequate to meet the demand of the empty calorie load. The laboratory method for identifying thiamine deficiency is by measuring it in the blood. If the result is reported by the laboratory as normal, the relevant symptoms produced by inadequate oxidation may well be ascribed to causes other than thiamine deficiency.

Hypothesis: High Calorie Malnutrition Induces Chronic Sympathetic Overdrive

I suspect that a common cause of hypertension is high calorie malnutrition, inducing a state of chronic sympathetic overdrive. It may be why obesity in children often foretells their rise in blood pressure. Perhaps another cause is the gradual diminution of oxidation associated with aging. There are genetic mechanisms that are turned on by hypoxia and these also may be activated by pseudo-hypoxia, e.g. thiamine deficiency.

Spontaneously Hypertensive Rats

Lipothiamin is a synthetic derivative of thiamine. Its biologic properties enable it to be used as a drug. A rat known as SHR (spontaneously hypertensive rat) is used as the animal model for studying the effect of antihypertensive drugs. Many years ago I took a group of these rats and treated them with Lipothiamin to see if it would prevent the rise in blood pressure that always occurs in these animals. There was a statistically significant difference between the experimental rats and the controls, indicating that this thiamine derivative did indeed prevent the spontaneous rise in blood pressure. This experiment is published in our book (Lonsdale D, Marrs C. Thiamine Deficiency Disease, Dysautonomia and High Calorie Malnutrition). It obviously requires human subjects to research the use of this completely non-toxic, nutrient/drug derivative but nevertheless provides us with solid clues about hypertension.

Conclusion: Diet Matters

It has been said that simplicity must be distilled out of complexity in order to make complex issues usable. The brain/body, whether we like to recognize it or not, is an “electrochemical machine” that must obey all the physical laws designed by Mother Nature. Health is governed by only three factors:

  1. Genetics: the enormous complexity is dictated by a code written in DNA. Passage from generation to generation makes mistakes and represents our inheritance.
  2. Stress: defined as anything that requires physical/mental defensive response. The response, designed for relatively short term action, demands a huge consumption of energy.
  3. Nutrition: this is the only one of the three issues that we can control. It must supply both fuel and the multiple factors that enable the fuel to be turned into energy.

We Need Your Help

More people than ever are reading Hormones Matter, a testament to the need for independent voices in health and medicine. We are not funded and accept limited advertising. Unlike many health sites, we don’t force you to purchase a subscription. We believe health information should be open to all. If you read Hormones Matter, like it, please help support it. Contribute now.


Yes, I would like to support Hormones Matter. 

Panic Attacks or Thiamine Deficiency?

2.7K views

As far back as 2022, I would get tingling and numbness in my arms. After eating I would get so tired that I couldn’t think or do anything. I would just stay in my seat like a zombie until it was time to go home. When I got home, I would sleep for an hour or two and then recover. This was in addition to the more than 8 hours of sleep a night. Even with all of that sleep, I could barely crawl out of my bed to get to work. I was always so tired.

In 2023, when I worked out, I had to take 10 minutes pauses between sets. I was completely drained. Eventually, it got so bad that I could no longer workout.  After about 6 months, my body decided enough was enough and I was hit with 3 days where I couldn’t get up from my bed. My muscles ached painfully and I felt incredibly sick. Eventually, I recovered though.

Fast forward to 2024 and everything took a turn for the worse. After a stomach bug, I developed IBS and SIBO. Out of nowhere, I started waking up in the middle of the night with insane panic attacks. My heart would pound all the time and my nervous system was stuck in fight or flight 24/7. I could only sleep 3-4 hours a night for many months. I had a lot of blood tests done, including all the vitamins, but they were serum, and I know now they were worthless. Everything came back normal except vitamin D which was low, so I started supplementing and staying in the sun. After a couple of months, somehow I recovered again and I thought that was it, the vitamin D was the culprit and I had solved it.

Surprisingly, for most of 2025 I was fine, in the sense that I didn’t have critical symptoms like before, except, there were times I would get so tired that I couldn’t think or do anything but sleep and my body felt incredibly heavy. Since I would recover quickly, I thought nothing of it. Also, during this time, I would wake up in the middle of the night, feeling extremely hot, and being irritable in a way that it not like myself. After about 20-30 minutes I would get really cold and instantly fall asleep again. This happened every night for many months. I would also be either extremely anxious or extremely tired during the day, alternating.

Persistent Tachycardia Considered Panic Attack

In 2026, I decided to start working out again. I managed to do so for 3 months before an array of symptoms, the likes that I never thought I could experience, began. They began with me being so tired that I almost fell asleep at the wheel. Then I would get home and instantly fall asleep from early in the day, until the next day. This lasted for about two weeks. After this, the panic attacks started. One night I woke up around 1 am in a full blown panic attack thinking I was going to die. I knew how to deal even with the worst panic attacks previous experience. I would just go out for a walk, and so I did that this time too. I walked for two hours but this panic attack was like nothing I experienced before. It didn’t stop. Eventually I ended up in the ER. I stayed there for 9h, during which time my resting heart rate did not come under 100bpm, and with the slightest movement it would jump to 140-150, even while laying down.

By morning this worried the ER doctor but the cardiologist that checked on me, and couldn’t find anything wrong after a whole bunch of tests. Even so, they kept me in the hospital for a few days for monitoring. Having similar experiences in 2024, where I was told by everyone that it was just anxiety and all in my head, I accepted it.

They gave me some pills to slow my heart rate down and I was discharged. That day, after more than 14 hours of non-stop tachycardia, my heart eventually slowed down. This was just the beginning of my declining health though. My sleep became restless and my heart felt like it was beating out of my chest for hours on end, again.

Since I went through something like this in 2024, I brushed it off to anxiety. I just tried to live my life and not think about it too much, but the symptoms persisted and diversified. I experienced frequent panic attacks that would wake me up from sleep. Sometimes, I would lay there in bed feeling a huge weight on my chest, unable to breathe properly. Other times, I would wake up and feel my muscles aching, heart pounding, and be so utterly tired that I just couldn’t move, no matter how much I wanted to. During that period, even minimal exertion would tire me very quickly.

Relentless Heart Palpitations, Insomnia, and Breathing Difficulties

On top of that, the insomnia and the feeling that my heart was pounding out of my chest was relentless, every night and day just non-stop. At one point, I was hit with a wave of tiredness like I had never felt before. I just couldn’t move. I couldn’t think and my heart was beating out of my chest and extremely fast. I was taking shallow and slow breaths and it felt like I was running out of oxygen. I thought I was dying and yet I was so tired that I couldn’t even call the ambulance. I couldn’t move at all. After about an hour, the episode resolved by itself, with me being completely normal.

In the same time period, I had two weeks in which my heart rate wouldn’t come down from 100, along with hours and hours of adrenaline surges, heat flashes, arrhythmias, and one episode in which my heart beat so fast that I was sure it was a medical emergency. My parents convinced me it was all in my head and so I just waited it out. Eventually it stopped, and I was so utterly tired that I simply passed out. I couldn’t stay awake anymore. This happened more times than I can remember: the utter tiredness, where I couldn’t think, move or do anything, but just lay there and watch it. It happened around friends, family, by myself, at random times.

Another time when I ended up in the ER because I felt my heart beating out of my chest, and my BP reader kept throwing errors when I tried to take my blood pressure, the doctor that listened to my heart was visibly worried, gave me a beta blocker which didn’t do much, and moved me from minor emergencies to major ones. Unfortunately, the doctor in charge of the major emergencies wasn’t so caring. He asked what I was doing there and said that I was wasting his time and released me. I went home with my heart beating out of my chest constantly, even while trying to sleep. I had many such episodes when I would wake up from dead sleep with my heart beating out of my chest, sometimes in a panic attack, sometimes not. Honestly, these episodes made me want to go to the ER each time, but I just tried to tell myself it was anxiety, because everyone was telling me that.

Of course all these symptoms made me seek many doctors and do a bunch of tests. As of now, I have been checked by four cardiologists, all of whom cleared me. I have had two thyroid panels, with autoimmunity and everything else, and they came back normal. I had a pheochromocytoma metanephrines test, all normal. During these episodes, my hands would tingle and so I checked Hb1ac. It was normal too. I only have slight insulin resistance because my glucose came at 99 fasting one time and 84 another. My insulin was 15 I think. Considering that I have been in a constant state of fight or fight for more than 3 months now, I think those results are pretty good. Really, the only thing besides the insulin resistance that came slightly elevated was my RBC which was 17.3.

All the doctors tell me that my symptoms are ‘all in my head’ and send me to psychiatry. I’m now tapering off the paroxetine that was prescribed, since it’s not helping at all. I never liked psychiatric medication. I only accepted to take it now because I was desperate.

A Horrible Diet

As a kid I used to eat a lot of candy and pizza. I lived off of breakfast cereals, pizza, and bread with ketchup; anything except natural foods. Honestly, I’m surprised I did not have health issues sooner. I am 29 years old now, and although I cleaned up my diet a bit over the years, maturing over the years, I still ate a lot of fast food.

What really tipped the scales was the SIBO. In the last 6 months leading up to all this, I craved carbs, and I ate a lot of them. Even if I wasn’t eating fast food all the time, white rice and potatoes were staples. I ate very little protein because it didn’t appeal to me anymore. With working out, I thought it was even more important to eat more carbs for energy. I did not understand why I would get so tired, to the point of not being able to continue, after 20-30 minutes, while my friends could do hours-long workouts. I couldn’t understand how they could have that much energy. I figured that was just the way I was built. I never considered diet.

Discovering Thiamine and Other Nutrients

More recently, I have learned about vitamin deficiencies, especially vitamins B1 and B12. Given my diet, I think these may be at the root of all of my symptoms. There may be additional deficiencies, but these two seem to fit.  A few weeks ago, I began supplementing with vitamins B12 and B1 (100 mg thiamine HCL), a multivitamin, and 200mg magnesium daily.

Surprisingly, ever since starting the thiamine, I have noticed that my heart recovers much faster. Where I used to wake up before with it pounding for hours on end, now it only pounds a few seconds then stops. I am still in an almost constant fight or flight state but it doesn’t go crazy like before. My heart used to fluctuate wildly. It could 80 one moment, 97 the next and so on. This could go on for hours.  Now, even if I have the surges, they are somewhat milder and don’t last as long.

Also, over these past two weeks, I have had days where I slowly recovered to feeling almost normal, in the sense that I wasn’t in constant fight or flight anymore, but then I would crash back to being exactly like before. It gives me hope that I might be on the right track, but the crashes are discouraging. Also, supplementing B1 seems to have fixed my IBS and SIBO. This is something I have been suffering with for more than two years and had tried everything to heal.

I have only been taking the thiamine for few weeks and I know that it is very little in the grand scheme of things but things seem to be improving slowly. I haven’t seen this pattern of recovery in the cases I have read. A lot of people seem to get a paradox reaction initially. I did not have that experience. I seem to get better and then backtrack again. Has anyone else experienced this pattern?

Also, I haven’t read any case stories where the person experienced adrenaline attacks that lasted hours and hours on end like I have. This is what made me think of pheochromocytoma initially. Maybe it was thiamine though. Does anyone have any insight on this?

We Need Your Help

More people than ever are reading Hormones Matter, a testament to the need for independent voices in health and medicine. We are not funded and accept limited advertising. Unlike many health sites, we don’t force you to purchase a subscription. We believe health information should be open to all. If you read Hormones Matter, like it, please help support it. Contribute now.

Yes, I would like to support Hormones Matter. 

Photo by Anna Shvets from Pexels

Lab Mice Get More Thiamine Than We Do

2.1K views

How much of our understanding of molecular mechanisms related to mitochondrial energy metabolism is wrong because the chow fed to the mice and rats used for this research is heavily supplemented with vitamins and minerals at quantities exceeding that of an equivalent human diet? I have been pondering this question for a few years now, but this morning the magnitude of the problem became clear when the pathway I had been studying was viewed positively when (hyper) activated in rodent research, but one that was clearly not so in humans. This is a pathway for which drugs had been designed to activate based upon the patterns identified in said research; research where the animals are fed a steady diet containing markedly higher concentrations of vitamins and minerals than humans will ever get, unless supplementing, and where the animals are sheltered from the bevy chemical stressors that deplete those same nutrients. So, on top of all of the other challenges associated with extrapolating data from animal research to humans, deriving data about the ‘normal’ behavior of molecular pathways that are incredibly sensitive to nutrient status and chemical exposures from well fed and environmentally isolated animals is extraordinarily problematic.

An Eye Opening Experience

As someone not trained in animal research, I never considered chow composition as influencing variable on all research. Sure, if the research question involved diet or nutrients specifically, the composition of the chow would obviously affect outcomes, but that there were would such stark differences in relative micronutrient content compared to humans is something I had not contemplated. A few years ago, however, I worked briefly with a foundation sponsoring some research into the various effects of thiamine supplementation on health. One series of investigations looked into genetic and metabolomic changes, along with variety of cognitive and behavioral measures, relative to a diet high in soybean oil, with and without thiamine supplementation. Since the foundation disbanded and the funding was cut, except for a few posters and abstracts, the results were never published. It was disappointing, because the results were remarkably enlightening – despite the issues with the chow.

That said, what struck me early on was the high intake of thiamine even in the control mice. In this particular set of experiments, the control mice were getting ~2.5mg/kg of bodyweight, while the mice in the two experimental ‘high thiamine’ groups were getting 51 and 102 mg/kg of bodyweight. This is an insane amount thiamine, even in the control group. By comparison, the average human eating a lot of processed and fortified foods, which is never a good idea, may get up to 4mg per day total and a large majority Americans get less than recommended daily allowance (RDA) of 1.1-1.2 mg/d. If he/she weighs 70kg that works out to between .02mg/kg and .06mg/kg daily – a minute fraction of what a lab mouse is given.

Why such a high intake of thiamine? It was explained to me that mice need more thiamine because they have a higher metabolism than humans.

Okay. Sure. But…

This never sat right with me, but not having the experience lab animals, I let drop and moved on. And then I began studying some molecular pathways that just happened to be influenced by thiamine and it occurred to me that conclusions drawn may not accurately reflect the true behavior of those pathways because of the chow fed to these animals. I began digging, and oh, what a mess this is. Not only do most of the published studies not list the vitamin concentrations in the particular chow used and make the assumption that all them contain equivalent amounts, they do not, but some may misinterpret the metrics. Most chow labels report nutrient doses in mg/kg of diet consumed by the animal. I suspect, in some studies they are using, or at least reporting, mg/kg of the animal’s body weight. Is the animal really consuming 5mg/kg of body weight or 5mg/kg of food? It is not always clear. Alternatively, other studies, including the one I reviewed for the foundation, scale the doses between the species using a multiple of 12. Apparently, this is to account for differences in body surface area. It is based upon the presumed rate of which organisms convert food into energy (heat dissipation) and it relies heavily on measures of body mass relative to caloric intake such that while larger animals consume more calories, their ‘metabolism’ by unit of mass is lower. This is a linear metric developed to estimate drug toxicity and may not accord with nutrient needs. Importantly, kcal burn and body mass are poor indicators of metabolic energy (here, here, here).

Reviewing methods sections from random studies that I have reported on in the past, there is no way to tell how much thiamine or other nutrients the animals actually consumed, unless the study was specifically designed to assess something related to thiamine. Even then, however, most studies assessing thiamine deficiency experimentally either use diets that include no thiamine and/or induce deficiency by administering anti-thiamine molecules like oxythiamine or pyrithiamine. That said, whatever the actual amount, even at the lowest possible intakes to prevent deficiency, the animals were consuming far more than a human would consume, and this is what troubles me most. Do lab rodents really require more thiamine than humans or have we simply underestimated human requirements? I believe it is the latter, but let us explore the basis for this argument before drawing conclusions.

Thiamine Requirements For Mice

According to the literature, the daily thiamine requirement for mice used experimentally ranges from ~2ug of thiamine per day up to 6ug per day. This does not sound like much unless we consider that mice weigh only about 25g. This means that a lab mouse gets at least somewhere between .08 -.48 mg/kg. In a 70kg human, this equals 5.6 – 33 mg daily. The human RDA or DRI (daily reference intake) is only 1.1-1.2 for women and men respectively, per day, and accumulating research shows that many people do not even get that much. Nevertheless, by these metrics, the lab mouse is getting 5 -~30x the amount of what is considered necessary for the average human, and as was illustrated previously, if other metrics are used, these animals get even more thiamine.

This begs the question, how are we calculating the metabolic needs of these animals such that they require more nutrients than we do? It turns out that, like anything, the answer depends upon what assumptions we make and how we factor those assumptions into the math we create to estimate those values. As I mentioned previously, the research I reviewed was using a drug toxicity metric that included surface area differences to calculate dosages between humans and mice. This, apparently, is a common metric. Others include different allometric variables like bodyweight and/or caloric intake to calculate metabolism. All of these are linear calculations where the change in one variable is assumed to perfectly and linearly correspond to the other. Biology is not linear, and at some point researchers recognized this and began multiplying the exponents of the body surface area. Needless to say, multiplying by different exponents changes the result dramatically. Whether it changed its accuracy, however, is questionable.

Just How Much Does Nutrient Intake Vary?

Per a review of such things, rodents get between .2 -.26ug of thiamine daily with three different chow formulas. The human equivalent dose (HED) for these values ranges anywhere from 2.8 mg/d to 69 mg/d depending upon which variables are included in the calculations.

For example, if the calculation considers kcal required per day to maintain function (a 25g mouse requires 15kcal daily, while a 70 kg human requires 2000 kcal per day), the human equivalent for daily thiamine intake would be from 2.8-3.3 mg – double and triple the current RDA/DRI. In contrast, if the calculation uses body weight as the key variable, the human equivalent would be 56-69mg per day, or more, as bodyweight increases. This is ~50x more than current RDA/DRI values.

Conversely, if we run the math backwards, the 1.2 mg per day thought to be acceptable male humans weighing 70kg equals only .017mg/kg or .0004mg per day total – clearly below the intake of the chow fed lab mouse (likely below that of the wild mouse), but also, well below what is required prevent deficiency in the mouse. Although I am focusing on thiamine, because that is what I know best, the issues with scaling dosages between mice and humans carries the same problems for each of the micronutrients.

extrapolations of nutrients from mice to humans overestimate the nutrient intake for a human, while scaling for humans to mice would underestimate nutrient intakes for a mouse and theoretically result in nutrient deficiencies.

I will ask the question again: are we really overestimating nutrient doses when scaling from mice to humans or have we fundamentally underestimated the nutrient requirements of humans all along?

The Development of Human Nutrient Requirements

The nutrient estimates of humans to which all animal research is compared is equally flawed but for entirely different reasons than those of animal estimates. Not only was metabolism not considered as variable in human dosing, and is thus not scalable in either men or women of difference sizes or from humans to mice or any other species, but our assumptions regarding the accuracy allometric models of metabolism are likely incorrect as well.

Nutrient requirements for humans were developed using food surveys of different populations. From the average caloric intake of an average man (70kg), thiamine and micronutrient consumption more generally, were estimated. Adequacy was determined purely upon the absences of observable symptoms of deficiency. A number just above the point at which deficiency symptoms were observable became the recommended daily dose. Doses for women and for pregnancy were largely guestimates based upon presumed differences between male and female size, activity levels, and calorie consumption.

There was never a mg/kg dosing strategy developed for micronutrients for humans, so there is no ability to scale relative to bodyweight, caloric intake, or surface area, as there is with lab animals. Neither were there ever any attempts to calculate the actual metabolic rates relative to micronutrient needs, then or since. The human micronutrient standards were developed based entirely on observational data and the absence of deficiency symptoms. Like many accepted medical truths, there was no math, just observation, some contention, but ultimately, consensus, and eventually, entrenchment – even when data suggested otherwise. Notably, there have been no changes to the RDA/DRI for thiamine for over 80 years.

That said, how do we really know if the thiamine requirements for humans are less than that of rodents? Could the recommended dose in humans, which causes deficiency in mice, also be causing deficiency in humans but the complexity of our biology and variability of our environment, paired with the longevity differences between the species, mask that deficiency – sometimes indefinitely? Possibly.

A Question of Metabolism

And then there is this: how do we really now that mice have a higher metabolic rate than humans? We don’t, and that is the other problem with scaling micronutrient needs between rodents and humans. We simply have no logical basis upon which to make these calculations. Certainly bodyweight, surface area and caloric intake differences are important, but those variables do not, in any way, address the fundamental question about metabolism, which is energy used. Energy is the basis for metabolism. Energy usage should be in the calculations we use to estimate nutrient requirements and it is not.

In study published in 2024, researchers did something almost heretical – they added energy variables to metabolic calculations and standardized for body mass, fat free mass, and environmental temperature to more appropriately estimate the energetic needs of rodents, versus other animals, versus humans. In doing so, they were able to calculate expenditures with a common metric that could compared across species: megajoules per day (MJ/d). From there, they calculated total energetic expenditure (TEE), resting energetic expenditure (REE) and active energetic expenditure (AEE).

By these estimates, humans have higher metabolic demands than rodents (and many other animals including apes). Per their research, the TEE of humans globally was ~27% greater than that of rodents. In the US, where the population is largely sedentary and overweight, TEE for humans was still 18% higher than that of rodents. While the AEE are largely the same between rodents and humans (~1% difference), the differences in resting metabolic needs are huge. Humans require 40-45% more energy at rest (US and global, respectively) than rodents.

Per the authors of the study, humans evolved to be an ‘energetically extravagant species’ due in part to our larger brains, which consume an awful lot of energy, even when we do not use them. None of the previous studies considered this variable (or several others) when calculating the presumed metabolic differences between the species.

If humans do indeed have higher metabolic needs than rodents, then shouldn’t we also need comparably higher micronutrient intakes to sustain optimal energetic capacity?

Comparing Well Nourished Mice to Malnourished Humans

To the original question that sent me down this rabbit hole, how do we know what we think we know about the activity of different nutrient- sensitive and nutrient – dependent proteins, either in isolation or within a pathway, when we study those proteins in animals that are very well nourished and the species to which we are extrapolating those findings is most decidedly not? And a question that I did not address, how do we know what we think we know when the study animals are never exposed to the bevy of nutrient depleting chemicals that the human is exposed to? We do not, and that is the problem.

This means that all of the conclusions I (and others) have drawn based upon animal research, where the animals receive far and above the nutrients that a human might, are likely skewed, if not entirely incorrect. That is a sobering realization, particularly when one considers all of the other problems associated with extrapolating data from lab animals to humans. Moreover, this is yet another reason why humans need more thiamine and other nutrients than are currently recommended by governmental entities.

We Need Your Help

More people than ever are reading Hormones Matter, a testament to the need for independent voices in health and medicine. We are not funded and accept limited advertising. Unlike many health sites, we don’t force you to purchase a subscription. We believe health information should be open to all. If you read Hormones Matter, like it, please help support it. Contribute now.

Yes, I would like to support Hormones Matter. 

Image: Rama, CC BY-SA 2.0 FR, via Wikimedia Commons

Beriberi is Alive and Well in America

25.8K views

Readers of this website must surely be aware that the American medical profession completely resists the possibility of vitamin deficiency as a cause of any disease in America. This is so deeply ingrained that anybody claiming such a diagnosis is considered a fool. This seems to be particularly addressed to the classic vitamin B1 deficiency disease, long known as beriberi. It is unfortunate that we use a Chinese word that, translated to English means: I can’t. I can’t. It is the expression of the profound associated fatigue. There is good reason for denial of its modern existence. It has always been common in countries where rice has been the dietary staple. It existed unrecognized for centuries. In fact, the incredible intricacies of this complex disease took many years to unravel, much of which was performed in China and Japan where there was an obvious interest. It was a series of important historical events that led to its final solution and the history is fascinating. I really think that it is an example of the proverb “those that forget history are condemned to repeat it”. For example, groups of factory workers developed their first symptoms of the disease together after an exposure to sunlight. “Epidemics” of the disease occurred in the summer months. It was only natural that the investigators at that time had concluded that beriberi was an infectious disease. Their search for the responsible micro-organism was a futile endeavor.

The explanation can only be provided from modern knowledge. We now know that ultraviolet light imposes a stress on the human body, requiring mobilization of energy in order to meet it. For example, a car requires more energy to climb a hill. The hill is an analogy for “stress”. The groups of workers described above were in a state of mild deficiency of the vitamin and the stress of the sunlight precipitated full-blown disease, simply because of lack of extra energy required to adapt to the stress. Thus, any form of stress has to be considered in relationship to genetic risk and nutrition if and when the symptoms of beriberi are precipitated.

With this preamble, let me describe some of the clinical experiences that I have been exposed to. First of all, I was lucky enough to be able to think about health and disease in my position in a multi-specialty clinic. I came to the realization that the human body is a wonderful “machine” where the coordination of 70 to 100 trillion live units called cells, depends on chemical energy that has to be transduced to electric energy in order to carry out cellular function. Not only that, I had recognized something that is taken for granted today, that brain cells have an extravagant use of energy. The case that precipitated my lifelong interest in thiamine (vitamin B1) was a six-year-old child who had intermittent brain disease that had confounded all the studies and tests applied in the search for a solution. To put it simply, it was a biochemical approach that showed that he and his brother had a genetically determined condition that, for the most part, allowed them to pursue a relatively normal childhood life. However, each episode of spontaneously resolving brain disease left a little bit more permanent damage. The disease was invariably precipitated by an exposure to a form of stress, represented by a simple viral infection, on one occasion by a mild head injury, and even after an inoculation.

With the help of John Blass M.D. who was working at the National Institutes of Health, we were able to prove that these boys represented the first example of what came to be known as vitamin dependency. In order to prevent brain disease, both of these children required enormous doses of thiamine, but if they were affected by any form of stress such as a viral infection, the daily dose of the vitamin would have to be doubled or tripled in order to prevent a brain disease episode. I came to understand that under these circumstances I was using thiamine as a drug and that it was not a matter of simple vitamin replacement. It was an early example of epigenetics, the relatively new science concerning the way nutrition and lifestyle affect our genes.

You have to understand a very simple idea: thiamine and magnesium are known as “cofactors” to a series of enzymes that represent the machinery of energy production. Both the cofactors are derived from nutrition and have to be bound to their enzymes by a genetically determined mechanism. Not only that: thiamine has to bind to a protein known as a thiamine transporter. The transporter is also genetically determined and conveys thiamine into the cell. All of this takes place in thousands of minute organelles called mitochondria. I refer to these organelles as the “engines” of our cells. That is why glucose can be compared with gasoline in a car engine. Like an excess of gasoline chokes the engine, an excess of glucose chokes mitochondria. Thiamine and magnesium can be compared to a spark plug that ignites the gasoline. Perhaps the reader can begin to understand that this vitamin deficiency disease can literally develop any symptom anywhere in the body according to the distribution of the deficiency and its degree. The brain, heart and nervous system are the most oxygen demanding organs so it is not surprising that they are the first to be involved in thiamine deficiency.

Additional Cases of Thiamine Deficiency

My colleagues knew of my interest and although I was a pediatrician I was asked to comment on the following case. A 67-year-old anesthesiologist at a hospital in Columbus, Ohio came down one day with “a heart attack”. He was subjected to catheterization of the heart that was found to be completely normal. Meanwhile, his son was a medical student and having researched his father’s symptoms, he claimed that the disease was beriberi. The patient was referred to Cleveland Clinic and I was asked to comment on the situation. I found that when he went to his garage to drive to the hospital he would be afflicted by a series of dry heaves. This alone would immediately call to question the possibility of thiamine deficiency. He would give the anesthetic for a series of cases, after which he would go to the pediatric ward and cut himself a large piece of chocolate cake. On returning home, he was too tired to eat dinner and would go to bed, only to repeat the performance the next day. He returned to Columbus with the advice that the patient’s son was correct. I never received a follow-up and don’t know how he was treated but I later heard that he had died. I suspect that he was, in fact, given thiamine in too large a dose that overwhelmed his fragile metabolism.

My next experience was with a brilliant pathologist who was well known in the specialty. She told me that she had extreme fatigue. In fact, a few days previously she had been driving to work but felt so ill that she had turned round and gone home. I discovered that she had a chocolate box in every room in the house. As she went around from room to room she would consume one of the chocolates in each box. I advised her to stop doing this and take a supplement of thiamine, whereupon she rapidly recovered. Note that this was purely a hedonistic urge and had nothing to do with her three meals a day routine.

Ondine’s Curse

A mythological character was a water nymph who supposedly lived in a puddle. She fell in love with a mortal who jilted her and she cursed him with the loss of automatic breathing when he was asleep. There is a disease known as “Ondine’Curse” where this form of breathing ceases, usually at night and the patient dies. So one day I was having lunch with one of the Ear Nose Throat surgeons who knew of my interest. He had seen a woman in the intensive care unit who had stopped breathing and he was called to put in a tracheostomy. He suggested that I should view the case. She was under the care of a rheumatologist and she had had a history of periods of unconsciousness as well as joint pain. In using my knowledge of chemistry, I was able to show that she had thiamine deficiency and began treatment with thiamine.

During her clinical recovery she developed a profound anemia which proved to be due to a deficiency of folate. The importance of this is that her brain was affected by thiamine deficiency but when she was treated with the vitamin, her energy dependent metabolism increased. This exposed a previously adequate sufficiency of folate related to her slow metabolism. The increasingly efficient metabolism stimulated by thiamine required more folate to meet the new demand. She was a chronic smoker that had contributed to the metabolic changes in brain function that precipitated a disease that had gone unrecognized for years. I remember visiting the rheumatologist to ask her whether we could conference the patient to expose this information. She obviously thought that it was an absurd idea and refused to consider a meeting of physicians for further discussion. I learned something else from this patient. She was discharged from the hospital taking supplements of thiamine and folate. When she returned for review, the paralysis in her legs was worse and she had developed a rash on her arms that may occur occasionally in association with deficiency of vitamin B12. It has long been known that B12 and/or folate deficiency could individually be responsible for pernicious anemia (PA). However it had also been known that folate supplementation could not be given on its own for folate deficient PA. It had to be given with vitamin B12 and I had forgotten this. I gave her an injection of vitamin B12 and over the next few days she had some fever and muscle pain but the rash disappeared and she felt better.

The Complexity of Treating Vitamin Deficiencies

I provide these details to show that an understanding of vitamin deficiency disease introduces complexities that require study. When she began receiving thiamine and became clinically worse, it would be easy to blame it as a “side effect” that required administration of the vitamin to be stopped. A physician must first of all have enough knowledge to suspect the possibility and then apply the necessary tests. Obviously, if the collective psychology refuses to accept that possibility, the complaints of the patient, together with the clinical observations of the physician, will be treated symptomatically without a full recognition of the underlying cause. My exposure to a case for which I had no medical responsibility provides an example, for I was merely a visitor. I heard from her that she had been diagnosed with heart disease. She went on to say that her heart rate had dropped to 30 beats a minute, an extraordinarily dangerous situation for which she had received the drug atropine. Atropine blocks the nerve mechanism into the heart, thus controlling the danger symptomatically. She had then been given a diuretic drug and she went through an agonizing 24 hours of almost continual urination. It was clear to me that this was a dramatic exposure of thiamine deficiency heart and nerve disease. She had in fact “wet beriberi”. It has been referred to as “wet” because of the profound collection of fluid in the body and that had been treated symptomatically with the diuretic. The point that I am trying to make is that although the patient had been treated successfully with drugs, the underlying cause had not been recognized. These are uncommon cases, but I am claiming that they are the end-point of years of nutritional and medical neglect and yes, medical ignorance.

Because thiamine deficiency has its major effect in the lower part of the brain, the earliest effects are those of a deregulated autonomic nervous system (ANS). The reader will remember that the ANS conducts the traffic of body organs under the command of the brain. It consists of two basic systems, one of which stimulates action and is called sympathetic. The other one stimulates rest and is known as the parasympathetic. An early symptom of thiamine deficiency is an overdrive in the parasympathetic system, whereas at a later stage of the disease there is usually an overdrive of the sympathetic system. Accepting this factor, it can easily be seen that the patient described above, whose heart rate was drastically slowed, had been endangered because one of the nerves to the heart had carried an overdrive of parasympathetic activity. This, accompanied by a huge collection of fluid in the body, was characteristic enough to look further for the ultimate diagnosis.

Common Presentations of Thiamine Deficiency: The Walking Sick

Looking back at the history of finding the solution to this disease, it is known to have a long morbidity and a low mortality but with a long life of chronic illness gradually leading to some form of mental or physical crippling. In the elderly patient it is often attributed solely to aging. In the 1940s an experiment was carried out in a group of human subjects who were provided with a moderately deficient thiamine diet. Their symptoms were characteristic of those that are presently regarded by most physicians today as psychosomatic. They were irritable, quarrelsome and experienced heart palpitations, headaches, loss of appetite, insomnia, diarrhea or constipation, chronic fatigue and/or intolerance to heat and cold. The vast majority of patients that I treated when I was in practice had a polysymptomatic presentation of this nature, many of whom had been doctor shopping without relief. I was dealing with what I call the “walking sick”, a large group of patients that are haunting the offices of physicians throughout America. Sometimes they had been given a named diagnosis but had not benefited from drug treatment.

The behavioral characteristics of children, particularly those with ADD or ADHD, are dietary in origin, often coupled with some form of genetic risk, not the least of which is superior intelligence. They are being treated symptomatically, but I offer the possibility that failing to recognize these symptoms as nutritional in character may be a failure to recognize them as the forerunner of chronic neurological or heart disease. It is a reflection of high calorie food ingestion overwhelming the action of non-caloric nutrients that enable the necessary synthesis of cellular energy for function, particularly in the brain. In our book “Thiamine Deficiency Disease, Dysautonomia, and High Calorie Malnutrition”, we note that our present culture is cursed with a hedonistic ingestion of high calorie malnutrition, responsible for much loss of health. In fact, I have suggested that it is the equivalent of what happened to the ancient Romans whose wine tasted sweet because of lead infiltration from the glaze used in their wine containing jars. They did not know that they were suffering lead poisoning. We don’t seem to grasp the danger of sugar. Each symptom, as it appears, is treated symptomatically with a medication. Rarely is there an interest by the physician concerning diet, particularly the ingestion of empty calories consumed socially. Given the challenge of hedonism, it seems to be part of life joy, particularly in the elderly, to indulge in all the dietary aspects of sweet, sweeter and sweetest. However, it is inappropriate to fail in recognizing the symptoms that might or might not develop as a result. If one or more of the many symptoms is recognized and the patient informed, it is then his/her choice to make the necessary changes.

We Need Your Help

More people than ever are reading Hormones Matter, a testament to the need for independent voices in health and medicine. We are not funded and accept limited advertising. Unlike many health sites, we don’t force you to purchase a subscription. We believe health information should be open to all. If you read Hormones Matter, like it, please help support it. Contribute now.

Yes, I would like to support Hormones Matter. 

Photo: Seated Youth by Wilhelm Lehmbruck 1917. Edited. Wilhelm Lehmbruck, PDM-owner, via Wikimedia Commons.

This article was published originally on April 11, 2019.

Rest in peace Derrick Lonsdale, May 2024. 

An Over Medicated and Chronically Ill Millennial

12.3K views

Frequent Infections, Antibiotics, and Asthma

As I’ve reflected on my current health challenges, I’ve come to the realization that I need to head back in time to my earliest years. Like many kids born in the early 90s, I was the first to receive a slew of vaccinations that were previously never given to children. I suffered from frequent “earaches” that led to multiple courses of antibiotics before kindergarten, and by the time I reached middle school, I was taking yearly courses of antibiotics for all sorts of things: colds, sinus infections, acne. It was around this time that I was also diagnosed with exercise induced asthma. I remember almost passing out in a lacrosse practice in 7th grade, and before I knew it, I was put on Advair (daily inhaled steroid) and was hitting the albuterol 2 or 3 times before a workout. My allergies also raged during this time.

Anxiety and Doctor Prescribed Benzodiazepine

I started getting increasingly anxious in early high school. I remember getting what I now know are symptoms of a panic attack in late middle school. Though part of this was due to the fact that I was hiding my sexuality (and hiding it well), I also realize that I had been slamming my adolescent body with drugs, vaccinations and the standard high sugar American diet for 14 years at that point.

My anxiety caused sleeping issues and I was placed on Ambien when I was 16. When I was withdrawn from that, the anxiety got worse (I know now it was Ambien withdrawal), and I was finally sent over to a psychiatrist. After listening to my description of panic attacks, she placed me on Klonopin, one of the most potent benzodiazepines on the market that should never be used for more than a few weeks. She told me to take up to four a day (an insane dose) and that like a diabetic, I needed GABA enhancement, and I would have to take these for the rest of my life.

At 17, I was buzzing on a benzodiazepine every day. I remember that it actually felt quite good and erased all worry. But then I began to experience one of the most terrifying side effects of long-term benzodiazepine dependence: I was getting dementia! I couldn’t remember things for tests or quizzes no matter how hard I studied. When I brought this up to the psychiatrist, she assured me that a little amnesia was a common benzodiazepine side effect, but that the benefits outweighed this. Essentially, giving a teenager dementia outweighed him having anxiety.

Benzodiazepine Withdrawal and Repeat Concussions

When I decided I needed to come off the benzodiazepine after taking it for a year, her instructions were to taper over one week and then jump. Now, this was 2010, and the internet was alive and well at that point. Upon doing just a little bit of research, I knew this woman was insane. All recommendations were that benzodiazepines needed to be tapered over the course of many weeks if not many months. I found a benzo support group online that became my lifeline for the next 4 months as I gradually weaned myself off the drug with the support of my parents and a new primary care doctor. Throughout this time, the one drug that I actually credit with saving me is marijuana. Without it, I’m not sure I would have done as well as I did getting off the drugs and then staying off of them.

I went right off to college that fall, which in retrospect was a miracle. I struggled a lot that first year. I was experiencing post acute withdrawal syndrome (PAWS) from the benzodiazepine and almost flunked out. I gradually improved but was still dependent on nightly marijuana to go to bed. In 2014, I finally stopped smoking weed and was 100% drug free.

That summer, I ended up getting my first concussion, though I suspect I had many others growing up as I played soccer and lacrosse. As if one wasn’t bad enough, I somehow ended up getting another the next summer in 2015 when I was at the beach and hit my head on a car door. I was later told by a neurologist that once you have a concussion, it becomes significantly easier to get a second, and then a third, and so on.

I had long suffered minor symptoms from benzodiazepine withdrawal that never went away, like tinnitus in my ears, an inability to take GABA drugs without reactivating withdrawal symptoms, and other neurologic symptoms that always made me feel “different.” The concussions added to this complex situation and I would have what I can only describe as seizures during times of stress or intense workout. It felt like my brain had electric current running through it.

Around this time, I also received the first injection for the Gardasil vaccine. I never followed up with the rest of them because of how off I felt that the first few days after getting it. Only recently have I learned about the severe damage that Gardasil can cause.

By 2016, I had been doing a paleo/plant-based diet and felt generally well, but the symptoms from both benzo withdrawal and my concussions persisted. In 2017, I started using CBD oil, and I found that it relieved a lot of the symptoms. It calmed my brain down significantly. I also began using Truvada (HIV medication) during this time as PreP. The one issue that never went away throughout all of this was my anxiety and panic. I was prone to situational panic attacks that felt like my fight/flight system was in total chaos.

A Complete Crash with Tinidazole

Despite feeling okay in 2018 and most of 2019, my whole world was turned upside down again in the fall of 2019. I contracted some sort of stomach bug that wasn’t going away, and my doctor placed me on a drug called Tinidazole, the sister drug of Metronidazole (Flagyl). I haven’t felt the same since that day.

The symptoms came on almost immediately. Dizziness, depression, increased anxiety, neuropathy in my hands and arms. I became convinced that I had ALS because my hands weren’t working right. It was also unlike me to ever assume something as terrible as a fatal diagnosis, but my brain was in total disarray.

Two weeks after taking the Tinidazole, I had to go back on antibiotics for wisdom teeth removal. Immediately after the surgery, I went into one of the most horrendous panic attacks of my life, in part because I had been injected with novocaine about 20 times. I had to be wheeled out of the doctor’s office because the panic had been so bad. Looking back now, there is a similar case study in Thiamine Deficiency Disease, Dysautonomia, and High Calorie Malnutrition.

Things only got worse. By the end of the penicillin, my body was in a total spiral. I began having daily panic attacks that I can’t even describe. My body temperature was low, my fight/flight system was in disarray, I was depressed, I couldn’t think clearly. There were nights when I wouldn’t sleep at all and be in total fight or flight mode. I now know that I was going through Tinidazole toxicity that had gradually gotten worse over a few weeks. Combined with the penicillin, it was a recipe for disaster.

The strangest symptom that has come out of this experience is hypoglycemia. My blood sugar is tanking to dangerously low levels during the day unless I am extremely diligent about eating. There have been a few times that I have almost blacked out. This isn’t a common symptom of Metronidazole/Tinidazole toxicity, but I don’t know where else it could have come from.

Where I Am Now

I’ve improved a bit, but I’m still having symptoms like dizziness, hypoglycemia, altered mental state, neuropathy and a total dysfunction of my fight/flight system.

Looking back at my long and complicated history, I’ve discovered a few things in my research:

  • Early and frequent antibiotic use is linked to anxiety and depression
  • I ate A LOT of sugar throughout my life and my thiamine stores were probably always being hit hard and my mitochondria have probably been fighting this battle my life
  • The benzodiazepine and Ambien have caused deep alterations to my nervous system/GABA receptors that became less noticeable with time but will never fully heal
  • Concussions cause a cascade of effects that damage mitochondria function and lead to other semi-permanent neurological issues
  • Truvada (PreP) also harms mitochondria
  • Tinidazole plummets your thiamine

Thiamine Deficiency and Problems With Paradox

I’d like to start Dr. Lonsdale’s protocol for high-dose thiamine, but I encounter painfully difficult paradox symptoms. I have tried to start with a low dose (less than 10 mg) twice now, and always end up having to stop because it gets so bad. The “heart attack” and “seizure” symptoms are simply too frightening and I’m not sure what’s actually going on in both my brain and heart. I’d like to find a functional doctor that could possibly work with me to measure what’s going on when I take thiamine.

I’m also in the process of working with doctors to run tests on my hypoglycemia issues.

The only other thing I’ve considered is a fecal transplant. Since I’ve been on so many antibiotics, I’m convinced that some of my issues may stem from altered gut microbiota.

Lots of people see improvement from Metronidazole/Tinidazole toxicity over the course of 6-12 months. But unless I can take action, I suspect my thiamine issue will remain.

We Need Your Help

More people than ever are reading Hormones Matter, a testament to the need for independent voices in health and medicine. We are not funded and accept limited advertising. Unlike many health sites, we don’t force you to purchase a subscription. We believe health information should be open to all. If you read Hormones Matter, like it, please help support it. Contribute now.

Yes, I would like to support Hormones Matter. 

This story was published originally on March 11, 2020.

High Dose Thiamine Healed My Fatigue. How Do I Navigate Pregnancy?

12.9K views

Downward Spiral, Upward Hope, Asking Advice

The year 2020 marked a big change for a lot of people. For me, it meant a downward spiral into intense fatigue, brain fog, and heart palpitations. Healing came in increments over the next three years until I found thiamine, which expedited my healing in six months. Now, I am considering pregnancy, but I need your advice. How do I navigate taking megadoses of supplements while growing a baby? How do I know when my healing journey is “complete,” and does that mean my supplement regimen ought to change? Any and all comments are welcome!

How It Started

It was early 2020 when I returned from a vacation from Thailand and got a stomach bug somewhere along the way home. I rested in bed a couple of days and mostly recovered, but had a lingering burning sensation in my stomach for the next month or so. I then noticed my stool started to smell strange and I experienced bloating after some meals. I went to the gastroenterologist, and within a month they had done an endoscopy and discovered erosive gastritis. I was put on a proton-pump inhibitor (PPI) and sucralfate to coat my stomach.

Two weeks on these medications and I felt immense brain fog and extreme fatigue, so much so that I felt like I would fall over in my chair at work. The fatigue hit me like a ton of bricks– I slept throughout the night and forced myself to take naps, and nothing helped shake the overwhelming fatigue. I took a few weeks off of work and tried to rehab myself at home, eating as much healthy food as possible (I was tracking 3,000 calories a day, which I felt I must need to get healthy again). I tracked all of my nutrients in an app and made sure I hit (and exceeded) the RDA for every nutrient (with the help of supplements). Still, things were not improving much, and I couldn’t even walk one stretch of the block without being utterly exhausted. It was during this time off of work where I felt so helpless and drained in every sense that I remember thinking, “this is what the beginning of dying feels like.” It scared me. But I honestly did not know what to do or where to turn.

A picture from July 2021 after a short hike. I felt horrible and my husband felt great :).

I knew the medications were not making me healthier (even if they made my stomach feel better), so I went off of them cold-turkey. The burning in my stomach became quite severe due to the rebound effect of getting off a PPI, but I pushed through, knowing that I needed my body to heal on its own.

The next three years brought incremental improvements, but still much suffering. Intense brain fog, insatiable fatigue that heightened post-exertion, and dysautonomic symptoms plagued me daily. I was waiting for a big break that seemed like it might never come. Little did I know, my time was coming in the spring of 2023.

How It Really Started

It would be easy to blame a stomach bug for all of my problems, but I now know that my nutrient stores have been taxed and depleted over many instances in my life. Here is a snippet of what led me to the crash:

– Childhood: Ear infections (antibiotics), chronic stomach aches, sugar consumption

– Adolescence: Traumatic brain injury (brain sheer, 3 days coma), mononucleosis, asthma

– Young adulthood: chronic UTIs (i.e., chronic antibiotics (including 3 separate Bactrim prescriptions and anti-fungals (fluconazole) afterward), several deaths in the close family (emotionally taxing), monthly naproxen for menstrual cramps, developed gluten sensitivity, shortness of breath (air hungry).

The stomach bug was simply the straw that broke the camel’s back. All of the stressors in my life (physical, emotional, etc.) depleted my body until it couldn’t retain a guise of “healthy” anymore.

My First (Unknowing) Megadose

Throughout the entirety of 2020, I experienced bloating and IBS symptoms. I managed the symptoms well enough with a low FODMAP diet, but one tiny piece of garlic, onion, etc. and I was ruined. I knew I wasn’t healed with this diet, but I didn’t really know how to heal, especially hearing that IBS is something you have to live with for the rest of your life. This scared me, but I wanted to see what answers may be out there.

I came across a study that claimed that the vast majority of participants taking a multivitamin, B-100 complex, and vitamin D3 were cured of their IBS within three months. It seemed like a miraculous and promising study, so I decided to try it myself. Lo and behold, around the three month mark, I was able to incorporate high FODMAP foods without experiencing bloating (it took a stretch of a few weeks to fully incorporate these foods as my body was adjusting).

Back then, I thought it was the vitamin B5 that was responsible for ridding me of bloating symptoms. Vitamin B5 is closely linked to gut health. Looking back now, I have a strong notion that I was helped due to the thiamine content in the B-100 + multivitamin. I megadosed without knowing it. And unfortunately, after about 4 months, I stopped taking the B-100.

My Second (Reluctant) Megadose

I visited a naturopath in the spring of 2021 to try to get more answers. I still had brain fog and fatigue, and had also developed a regular heart palpitation every ~15 minutes, which coincidentally happened after my second round of a certain vaccine. The naturopath prescribed many supplements, one of which was 150 mg of iron per day. I was shocked by this and thought that was wayyyy too much and was scared I would get iron overload, but he assured me that with my ferritin levels at a 9, it was desperately needed.

Within a week of supplementing with iron, I felt a big boost in energy and felt I had found the answer that I had been waiting for. While it did help, I reached a threshold of improvement that did not change despite continued supplementation with iron for over 1.5 years. The iron supplements did help with my heart palpitations, but I still had brain fog and fatigue. On a scale of 1-10, with 1 being my lowest point in the summer of 2020, iron brought me to about a 4.

My Third (Homecoming) Megadose

So time went on and I tried every supplement under the sun. I focused on vitamins and mitochondrial nutrients such as L-carnitine, alpha lipoic acid, CoQ10, and others, and I was able to live a life that looked kind of normal. But it didn’t feel normal. I was obsessed with finding the answer(s) to this dark cloud that had been engulfing me the past few years.

Until one day, just six months ago, in late April of 2023, a recommended video popped up on my YouTube homepage that changed my life. The video was from a smart lad named Elliot Overton talking about thiamine deficiency.

You probably know how the story goes.

I started with benfotiamine, because I could get it at the store, while I waited for my TTFD to arrive in the mail. I kept trying to press how much I could tolerate without too much headache/fatigue/brain fog, and I honestly can’t remember if I noticed an improvement in those first few days. Once my TTFD arrived though, within two days of supplementing I felt a rushing wave of beautiful relief come over me.

Finally. Finally! My answer had come. I wasn’t immediately better, but I knew improvement was on its way. It wasn’t long before I came across Hormones Matter, which brought me so much useful information! I began sleeping better. My dreams were more vivid. I was able to sweat more easily, something I didn’t know I had lost until it returned. The volume was turned down on my anxiety and breathing deeply was easier.

It took some adjusting and playing around with dosing to find out what would help me. At first, I could only consistently tolerate one 50 mg TTFD pill every-other day, or I would get a racing heart and worsened fatigue. I also noticed that after about a week of taking TTFD, I would start to feel drained, as if it wasn’t giving me that feeling of relief anymore. So what worked for me was to cycle TTFD, thiamine HCL, and sulbutiamine for one week each. That kept my feelings of “relief” heightened. I pretty much abandoned benfotiamine because, well, I had other stuff that was working and I didn’t want to change my routine.

Within about a month, I was able to take one TTFD per day. As time went on, I kept bumping up all of my doses for each type of thiamine. I would basically take a day to test how much I could handle, then try to sustain that higher new dose. By the end of July, I was taking 5-6 TTFD and 10-ish thiamine HCL (100mg each). I am not exactly sure with the doses. I believe I only made it up to 400 mg of sulbutiamine. At a certain point mid-summer, I dropped the sulbutiamine because it seemed to be making me feel depressed, even though it helped when I first began taking it. I also dropped the thiamine HCL. I felt that TTFD was more powerful and so I stuck with it. I no longer experienced a drop in “relief” symptoms and was able to take TTFD only without any adverse effects.

Somewhere between then and now I have worked myself up to 12-14 TTFD per day (600-700 mg). I have very little brain fog or fatigue and can work out without being drained the next several days. I feel pretty darn good most of the time. Of course, there are ebbs and flows, but overall, I am doing well.

In addition to the thiamine, I have been taking lots of support nutrients too, such as magnesium, multivitamin/B complex, selenium, molybdenum. Another major helper for energy has been 10-15 grams of creatine monohydrate per day. I eat a whole-foods diet with no added sugars.

My Fourth (Aha!) Megadose

Recently, I came across information by Linus Pauling, a Nobel Prize and Peace-Prize winner who championed high-dose vitamin C therapy for minor and major illnesses. I caught a cold around this same time, started high-dose vitamin C therapy, and was absolutely sold with the idea, as none of my symptoms really developed into much at all. While I’m not convinced of taking megadoses of vitamin C every single day, I am certain it is helpful during times of sickness.

Then I read about Orthomolecular Medicine, which uses high-dose vitamins for treating diseases (chronic, communicable, genetic), and it all made sense! I felt as though I had uncovered a secret to the world! I wouldn’t have believed it had I not experienced the “miracles” of megadosing first-hand, but now I realize that most, if not all, diseases can be treated with the right dose of specific nutrients for the right amount of time. I also realize that those doses are higher doses than what we think! And higher still! Yeah– even higher. And longer– yes, keep taking them. I don’t mean to oversimplify people’s illnesses, but rather to illustrate the power of high-dose vitamin therapy.

Then Versus Now

My healing journey is not quite over. I have tested positive for antinuclear antibodies since 2020, and my latest test (October 24, 2023) still tested positive (qualitative only). Finding out these results was a little disheartening, as I really thought my results would be negative. I have had less energy and some mild dysautonomic symptoms since receiving those results, which either means a) the power of suggestion has really gotten to me or b) I switched to thiamine HCL around the same time and it is not as effective as TTFD.  I am leaning towards the latter, but I wanted to give HCL more of a shot because the amount of TTFD I’m taking per day is getting expensive! And as a more recent update, the last two days I’ve tried Benfotiamine, which I have been very pleased with— my energy seems to be much better than with thiamine HCL.

I also just started alpha-GPC as a new supplement.

Here is some physical evidence that I am healing:

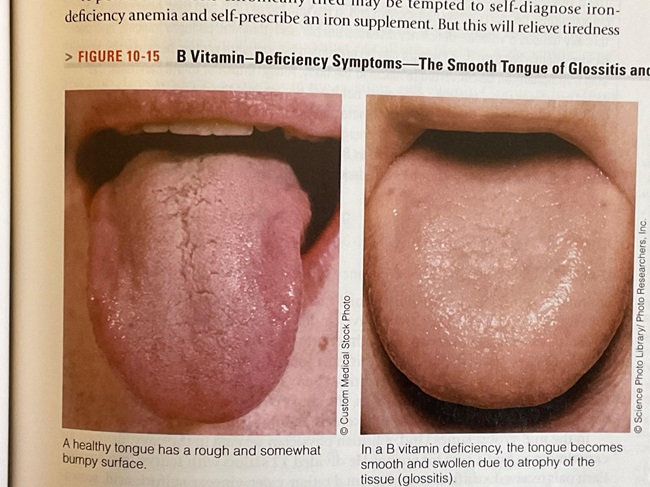
In one of my textbooks, I found that a B-vitamin deficiency (doesn’t say which B vitamin) causes a smooth tongue.

tongue vitamin B deficiency
Figure 1. Textbook images of vitamin B deficiency affecting the tongue.

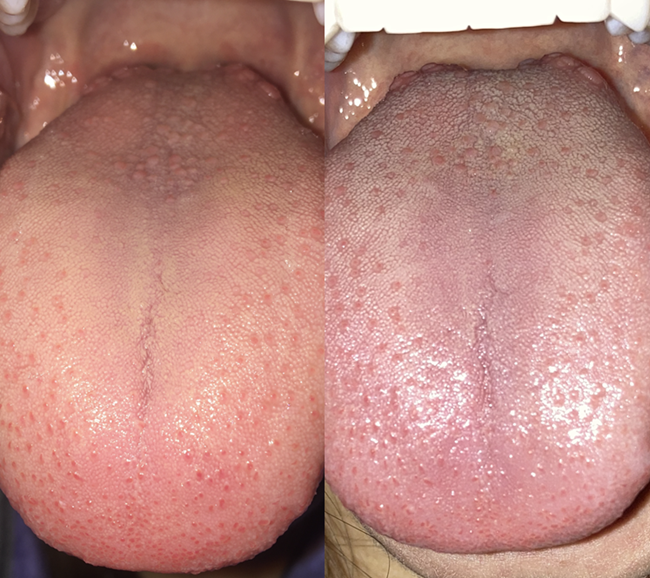
I took a picture of my tongue in October 2020, and the second picture in October 2023. Notice the more prominent fuzzy (white/gray) projections in the second picture. These projections are quite blunted in the first picture.

Vitamin deficiencies and the tongue
Figure 2. Photographs of my tongue. Left: October 2020. Right: October 2023. The most prominent changes are on the sides and at the back of the tongue (more “fuzzy”). I believe these changes are in large part due to thiamine.

Hope for The Future

My husband and I are excited about the possibility of getting pregnant, especially now that I am feeling so much better. Having a child has been a long-time dream of mine, and while I was struggling with my health, I wasn’t sure if that dream could come to fruition. So now being in the place I’m in, I’m thrilled that we can think about having a child. I’ve had to tap the brakes on my excitement, because I don’t want to potentially cause any harm to a growing baby due to my megadosing of thiamine. So, I have a couple of questions.

Asking Advice:

  1. Does anyone have any research, personal, or hearsay information regarding the safety of megadose thiamine during pregnancy? If so, did the type matter (TTFD, thiamine HCL, Benfotiamine)?
  2. What is the maximum dose you reached for TTFD/thiamine HCL/Benfotiamine?
  3. Have any of you had any experience with weaning off of thiamine or stopping cold-turkey? I have gone a few days here and there without supplementing with no issue, but not longer than that. If so, was your health maintained, or was there a maintenance dose that sustained you?
  4. How did you know it was time to stop/decrease thiamine (if at all)?

Closing Thoughts

I just want to extend my heartfelt empathy for all of you who may be experiencing health struggles. Before these past few years, I sometimes had the arrogant thought that people could just be healthy if they avoided sugar and exercised. I thought their health struggles were their “fault”, to an extent, but I now recognize the complexity of health and the desperation in trying to find it once it is lost. I understand what suffering is and the feeling that there is no escape. I understand the feeling that no one truly knows what you are going through, even though they extend love and patience with you. I get it, and it sucks so much that this has to be a part of the human experience—but I have also experienced hope. A real hope. A hope that delivers what it promised. I could not have known even a day before taking thiamine that my time of deliverance had come. So please do not give up hope. Your day is coming.

We Need Your Help

More people than ever are reading Hormones Matter, a testament to the need for independent voices in health and medicine. We are not funded and accept limited advertising. Unlike many health sites, we don’t force you to purchase a subscription. We believe health information should be open to all. If you read Hormones Matter, like it, please help support it. Contribute now.

Yes, I would like to support Hormones Matter. 

Photo by Tim Mossholder on Unsplash.

This story was published originally on November 7, 2023.

Sleep Requires Energy

31.6K views

It is widely believed that almost no calories are used during sleep. That is incorrect: while the body rests during sleep and energy consumption is not high, it is a long way from zero. A convenient way to measure energy use is known as the “metabolic equivalent” (ME). This is defined as the rate of energy used by a person sitting and awake, the “resting metabolic rate”.  A person riding a bicycle may be using five MEs; a runner, nine or more. A sleeping person uses about 0.9 MEs, so we burn calories when we are asleep about 90% as fast as while sitting on the couch watching television.

Energy conservation is important in sleep, but it’s expenditure is still required. It has been proposed that sleep is a physiological adaptation to conserve energy but little research has examined this proposed function. In one study, the effects of sleep, sleep deprivation and recovery sleep on the whole-body, total daily energy expenditure was examined in seven healthy participants aged 22+/-5 years.  The findings provided support for the hypothesis that sleep conserves energy and that sleep deprivation increases total daily energy expenditure. I read somewhere that an enthusiastic young astronomer decided that sleep was unnecessary and used his telescope for 13 nights without sleeping during the day. He became extremely ill, thus showing the importance of sleep in survival. The recognition that sleep is one of the foundations of athletic performance is vital.

Research in the general population has highlighted the importance of sleep on neurophysiology, cognitive function and mood. In a post on Hormones Matter, we reported several young people who had a post Gardasil vaccination crippling condition that turned out to be due to thiamine deficiency. All of them had been exceptional athletes and students before the vaccination. We concluded that the brain energy requirement for exceptional people put them at greater risk of succumbing to stress if their capacity for MEs was limited, either for genetic or nutritional reasons. We assumed that their thiamine deficiency before vaccination was marginal and either asymptomatic or producing trivial symptoms ascribed to other “medically more acceptable” causes.  The stress of the vaccination required an energy dependent adaptive response that precipitated fully symptomatic thiamine deficiency.  You might say that they were “weighed in the balance and found wanting” as the proverb says.

The Stages of Sleep

Sleep is a complicated process. The first sensation is known as “sleep latency” and registers the time taken from eye closure to falling asleep. The sleep cycle is then divided into five stages, each cycle lasting approximately 90-120 minutes. Stage one is known as light sleep. In stage 2 the brain is resting the parts used when awake. Stages 3 and 4 are deeply restorative. Stage V is known as rapid eye movement (REM) sleep and may be the most important part. Movement of the eyes behind closed lids is observed. The autonomic nervous system is activated for unknown reasons. It is in this stage when we dream and most sleep disorders occur.

Circadian Rhythm

The word circadian means “about 24 hours”. The circadian clock is a complex, highly specialized network in the brain that regulates its day/night metabolism and is a key for metabolic health. It is modulated by behavioral patterns, physical activity, food intake, sleep loss and sleep disorders. Disruption of this clock is associated with a variety of mental and physical illnesses and an increasing prevalence of obesity, thus illustrating that it is dependent on energy balance (production/consumption). Reduced sleep quality and duration lead to decreased glucose tolerance and insulin sensitivity, thus increasing the risk of developing type 2 diabetes. In other words there is a close link between circadian rhythm and available energy . I have seen patients who were unable to take the night shift at work because they were unable to adapt. The increase in obesity has been paralleled by a decline in sleep duration but the potential mechanisms linking energy balance and the sleep/wake cycle are not well understood. An experiment was reported in 12 healthy normal weight men. Caloric restriction significantly increased the duration of deep (stage 4) sleep, an effect that was entirely reversed upon free feeding.

Sleep Apnea

This condition is fairly common in the United States and is probably generally fairly well-known by most people. The patient stops breathing during sleep and may repeatedly awaken with a start. The disease was discovered because a woman reported that her husband kept waking up with a start because “he was affected by an evil spirit”. Fortunately, the physician took her seriously and it led to the studies that determined its cause. Many patients with, or at risk of, cardiovascular disease have sleep disordered breathing (SDB). These can be either obstructive because of intermittent collapse of the upper airway, or central because of episodic loss of respiratory drive. SDB is associated with sleep disturbance, hypoxemia, hemodynamic changes and sympathetic activation. Brainstem dysfunction combined with heart disease is the hallmark of the thiamine deficiency disease, beriberi.

What that means is that there are two types of sleep apnea. In the obstructive type, the tongue falls back into the pharynx and blocks the airway. In the one where there is loss of respiratory drive, the centers in the brain stem are compromised. It is these centers that completely take over the control of breathing when we are unconscious as in sleep. If their supervisory mechanisms fail, breathing ceases. Carbon dioxide concentration increases and stimulates the brain controls that restart breathing. Occasionally these mechanisms are so sick that breathing does not restart. Hence a form of  nocturnal sudden death follows. When we are awake we can override these centers and control our breathing voluntarily. Obesity and obstructive sleep apnea have a reciprocal relationship depending on the regulation of energy balance. When I was in practice I treated several patients with sleep apnea using large doses of thiamine. Because of this I hypothesized that the association of dysautonomia with so many different diagnoses is because of loss of oxidative efficiency and subsequent disorganization of controls that are mediated through the limbic system and brainstem. I came to the conclusion that energy deficiency in the brain was the core issue.

I recently had a letter from the parents of a then five-year-old child who came under my care 35 years ago. She has a genetically determined disorder that affects energy balance and I had treated her by dietary restriction and providing non-caloric nutrients. They informed me that she was doing very well. The condition is known as Prader Willi syndrome, a terminology that indicates that nothing was known about its cause when it was initially described. Today, 10 studies have provided evidence that total energy, resting energy,  sleep energy and activity energy expenditure are all lower in individuals with this syndrome. Dietary discipline and nutritional supplementation had paid off.

An Explanatory Analogy

You may think that comparing the human body with an automobile is manifestly absurd, but the principles that I will use in the analogy are simple.

Fuel

First of all, both use fuel: gasoline is the fuel for a car, but it must be calibrated to the design of the engine, giving rise to the gasoline choices at the pump. Although different forms of human food may be compared to gasoline choices, the primary fuel for our cells is glucose and this is particularly true for the brain. Glucose, a carbohydrate, can be synthesized in the body from other components in the diet and different diets are sometimes used therapeutically. Unlike the car, the human body must derive its “spark plug”  from the food and is the basic reason why organic, naturally occurring, food is a necessity. The food industry cannot imitate or replace it.

Engine

The engine in a car burns gasoline to create energy. It requires spark plugs to ignite the gasoline and waste gases are eliminated through an exhaust pipe.

Every cell in the human body has an “engine”. Without going into details this is known as the Krebs cycle (named after its discoverer). Its objective is to produce energy and glucose has to be “ignited” (oxidized). The oxidation process, while releasing energy, gives rise to carbon dioxide (the “ash”) that is eliminated in the breath. Energy is stored in an eletrochemical form known as adenosine triphosphate (ATP).The nearest parallel would be a battery. It releases an electrical form of energy that is then used for function. Whether we like to recognize it or not, we are electrochemical machines and the only way that we can preserve or retrieve health is by furnishing the complex of ingredients that enable food to be converted into energy.

To continue the analogy, when you put your car in the garage and turn off the ignition the car is technically “dead”. Obviously, we are unable to do that with the human body, but let us make a simple comparison. Supposing for some reason it was desirable to keep the car “alive” when it was in the garage. The engine would continue to run and it would be consuming fuel. Because the body requires energy to remain alive, the “engines” have to continue running, even when we are asleep. This does make sense for the consumption of energy when we are asleep———it keeps us alive !

Transmission

The energy developed from burning gasoline has to be transmitted to the wheels in order to produce the normal function of the car, which is the ability to move. The transmission is a series of levers that are interconnected.

The same is true in the human body, but it is biochemical in nature. A series of energy consuming enzymes use the protein, fat and carbohydrate to build the diversity of tissues that make up the body. Throughout life, cells are destroyed and replaced, so this is a continuous process of energy consumption and repair. Every physical movement, every thought and emotion, consumes energy. Like the transmission in the car, the energy produced by the citric acid cycle engine is consumed in every movement of the body, every thought occurring in the brain and every emotion.

Chassis

The body of a car is just a container on wheels designed to carry around human beings. Its sole function is to move and until we have driverless cars a human being must be the driver.

In comparison, the body of a human being is merely a chassis that carries the brain around. It might be said that the brain can be compared with the car driver and every function of the body is under the command of the brain. Another analogy that I have used is an orchestra where the brain is the conductor and the organs are banks of instruments in which the cells come under the command of the conductor.

Putting It All Together

The 2019 Nobel prize has just been awarded to three scientists who have discovered how our body cells respond to low concentrations of oxygen (hypoxia). The reaction of medical scientists is very positive since this discovery will certainly be applied to the treatment of many diseases. Apparently scientists are already trying to find drugs that will influence this effect. For example, it has long been known that hypoxia will introduce inflammation. My forecast is that the use of nutrients will often correct the genetics by epigenetic mechanisms and this is already under way.

I found the Nobel prize extremely interesting because of a little-known phenomenon that was described by the early investigators of the vitamin B1 deficiency disease, beriberi. They had found in this disease that the arterial concentration of oxygen was low while the venous concentration was relatively high. Arterial blood carries oxygen from the lung to all the tissues of the body. It has to be unloaded into the cells that then use it to produce energy. The venous blood then returns to the lung to be loaded again with oxygen. A relatively low arterial oxygen reflects an inadequate loading at the lung tissues, while a relatively high venous oxygen indicates poor utilization by the cells to which it is delivered. This means that thiamine (vitamin B1) is an essential catalyst in the delivery of oxygen to the tissues. Its deficiency induces gene expression similar to that observed in hypoxia and has been referred to as a cause of pseudo-hypoxia (false hypoxia).

The heading of this article is that sleep requires energy, but I am making the case that being alive and well simply means that oxygen is being consumed efficiently, as long as the “blueprint” of DNA is healthy. It strongly suggests that hypoxia and/or pseudo -hypoxia are the underlying causes of disease and may explain why thiamine and its derivative are such important therapeutic agents.

We Need Your Help

More people than ever are reading Hormones Matter, a testament to the need for independent voices in health and medicine. We are not funded and accept limited advertising. Unlike many health sites, we don’t force you to purchase a subscription. We believe health information should be open to all. If you read Hormones Matter, like it, please help support it. Contribute now.

Yes, I would like to support Hormones Matter. 

Image by freestockcenter on Freepik.

This article was published originally on October 14, 2019. 

Rest in peace Derrick Lonsdale, May 2024.

Energy Loss as a Cause of Disease

19.9K views

I graduated from London University in 1948 and retired at the age of 88 years in 2012, so I have seen some remarkable changes in the practice of medicine. I have entered many reports on this website, detailing what should be a medical revolution. One of the best professional associations that I have ever made has been with Dr. Chandler Marrs, the editor of Hormones Matter. Both of us have tried hard for years now to explain the details of our experience, hoping to reach those many individuals who are being misdiagnosed and treated extremely badly. My recent experience has come from retiring in an excellent retirement home.

I am surrounded by people of my age, many of whom are taking numerous medications to treat their symptoms. The most recent example was in a gentleman who has been in and out of hospital several times with a set of symptoms whose origins are clearly due to cellular energy deficiency. When approaching him as a friend and asking him how he is faring, he told me that his list of symptoms remains as a medical mystery. In addition, two women, with whom I had become acquainted, had symptoms that were similar to his. One of them passed away without a diagnosis and the other one is presently being treated symptomatically. The reader might well ask the obvious question as to what happens if I should state an opinion. The answer is very simple; the offered explanation would fall on deaf ears. Unfortunately, this is eminently predictable and is the major reason why innovation that contradicts the medical standards of the day is regarded as heresy throughout history. Of course, “new” concepts must be backed by evidence to become accepted. We are trying to provide the evidence on this website for defective cellular energy as a major cause of disease.

Heresy in Medicine

I am pretty sure that I may have recorded the story of Dr. Semmelweiss on this website but it is a story so poignant that it is well worth repeating. It is a story that illustrates the difficulty of introducing innovation in medicine, or indeed anything new. Semmelweiss was a German Hungarian physician who lived before the discovery of microorganisms. He presided over an obstetrics ward in which there were perhaps 10 beds on one side of the room and 10 beds on the other. The physicians of the day would come in and deliver their patients without washing their hands or changing their clothes. It is difficult for some people to comprehend the total lack of any form of hygiene that doctors practiced before microorganisms were discovered. Semmelweiss observed that the physicians would often come into the ward directly from the morgue and concluded that they must be bringing something in on their hands that caused the patient to die from child-bed fever, as it was then called. From this observation, he organized the first controlled experiment in medicine. He directed the physicians on one side of the ward to wash their hands in chlorinated lime before they delivered the patient. The physicians operating on the other side of the ward carried on in the same old way.

The results were dramatic as we would expect today. Child-bed fever was reduced by 85% when the physicians washed their hands. The medical profession, including his colleagues, said that “because Semmelweiss could not explain what was on the hands of the physicians, his explanation was unscientific”.  It is important to note that they simply ignored the obvious benefit. He was discharged from his job and excluded from the hospital. He died as a pauper in a mental hospital.

The major point is that the concepts of the medical profession of the day were completely wrong,  He had clashed with the current medical model that was then accepted by mainstream medicine as “the truth”.  If we apply this lesson to today’s model of medicine, it is impossible not to wonder if the outstanding principle of the use of pharmaceutical drugs in medical practice is fundamentally wrong. Is treating symptoms without addressing their underlying cause scientifically justified? A glance at the Physicians’ Desk Reference that supplies information on the many prescription drugs available might put off the reader’s use of a prescription. For each drug there is a short description of its use, often with an admission that its action is only partly understood. Then follows a page or two describing its side effects. Does this not suggest that the use of pharmaceuticals to treat symptoms causes more problems than it solves? Are we approaching another Semmelweiss moment in medical history?

Envisioning an Alternative Approach

I envision the profession of medicine as like a traveler, hoping that the road leads to the best solution in the treatment of disease. For my analogy the traveler comes upon a fork in the road with a signpost. One sign says “Kill the Enemy“, (referring to the discovery of infecting microorganisms) and our traveler takes that road because the sign for the other fork is blank. “Kill the enemy” became the first paradigm (a model accepted by all) in medicine. We had to find means of killing bacteria, viruses, cancer cells or any other attacking agent and many years were spent in trying to find ways and means of doing this without killing the patient. The information was hard won and a lot of patients suffered untold hardship and even death until the discovery of penicillin. This in itself “proved that the correct fork in the road had been chosen”. As we know, this discovery led to the antibiotic era, but even these drugs are running into new problems.

To continue the analogy, our traveler goes back to the fork in the road and finds that the other sign has now been filled in. It reads “Assist the Defenses” and I believe that it should represent a new paradigm. Louis Pasteur and his colleagues discovered the disease producing microorganisms, but on his deathbed he is purported to have said “I was wrong, it is the terrain that matters”.  He meant that the terrain represented the defensive functions of the body that should be assisted.  Perhaps he formulated what I believe must be the second paradigm in medicine.

The Second Paradigm

How should we approach the introduction of this concept? It seems to me that the problem is that few people are aware of the basic principles of body function so I must provide another analogy that I have used before in Hormones Matter. The human body can be compared with a symphony orchestra in which part of the brain represents the conductor. The organs represent the banks of instrumentalists that make up the orchestra. Like the instrumentalists who, although they are experts in their own right, still have to obey the conductor, the cooperative function of all our cells must obey the automated signals from the brain to play the symphony of health. Each of us comes with a “blueprint” that is our inheritance and although we are all the same in principle, we are all uniquely different because of accidental or inherited variations in the “blueprint”. The autonomic (automatic) nervous system, controlled by the lower part of the brain, coordinates the function of organs in the body, behaving like a computer. It receives sensory information, enabling it to receive from and send signals to those organs, thus collectively playing the symphony. The endocrine system consists of a group of glands that produce hormones. Their function, also under the command of the brain, is to release the hormones that travel in the bloodstream to the organs and are thus signaling agents.

The voluntary nervous system, controlled by the upper part of the brain, gives us what we call willpower. The voluntary and autonomic systems are completely separate but have many connections, so some of the reflex activity conducted by the autonomic system can be influenced and overridden by an act of will. Perhaps the best example is the fight-or-flight reflex that is activated by a sense of danger but can be modified voluntarily. For example, the reflex response to an insult might result in violence if it is not modified by the voluntary system. Assuming that the blueprint provides all the machinery of survival, all it requires is energy.

The Production and Consumption of Energy

We cannot survive without food and water. There is, however, an overall tendency to ignore the appropriate nature of the food, in spite of the fact that it provides the fuel that gives us energy. Taste is the dominating influence, driving sales for the food industry without an appropriate consideration of calorie/micronutrient balance. It is clear that “vitamin enrichment” has hoodwinked us. Chemical energy is liberated from oxidation of fuel (food), but it must be transduced in the body to an electrical form of energy that enables us to function. The electrocardiogram and the electroencephalogram are both tools that identify the electrical nature of this function. The human body is well equipped with an enormously complex system of defense but its complexity requires energy that has to be increased when a person is under any form of physical (trauma, infection, severe weather etc) or mental (divorce, grief, business deadlines etc) stress. It is very important to think of stress as a “force” to which we have to adapt. The lower part of the brain, acting like a computer must automatically organize the complex defense machinery, including the immune system, so its energy requirement exceeds that required by the rest of the body and must be automatically increased to meet the required response to stress. What we call the “illness” (fever, swollen glands, inflammation, etc.) is evidence that the brain has gone into action to generate a defense. In fact, war is declared and the result is recovery, death, or prolonged chronicity where the attacker has not been completely defeated. A nutritionally deprived individual cannot muster the energy to initiate defensive action and may explain why stalemate or the stress of vaccination can be evidence of failure to adapt.

Of all the aspects of health maintenance, exercise, appropriate rest, socialization and fulfilling job assignment, perhaps nothing is more important than the nature of the food. Genetics, stress and nutrition are visualized as the “three circles of health“. I want to illustrate this relationship by retelling an incident that we reported in “Hormones Matter” a few years ago. The mother of an 18-year-old girl reported by email that her daughter had received the HPV vaccination (to increase immunity against the virus associated with cancer of the cervix) four years previously. Throughout the four years she had been more or less crippled by a condition known as postural orthostatic tachycardia syndrome (POTS). She had been seen by many physicians without any success. Her mother did her own research work and had come to the conclusion that her daughter had the vitamin B1 deficiency disease known as beriberi and she wished to prove it. A blood test clearly showed that she was correct. Because of this, several young people who had also suffered from POTS following the HPV vaccination were also found to be thiamine deficient. One young woman who had not received the vaccination also had POTS and was found to be thiamine deficient. One of the observations that had puzzled the parents of these young people was that, without exception, each of them had been recognized as an exceptionally good athlete and student before they had received the vaccine. We deduced from this that a superior brain was more likely to consume  more energy than someone less well endowed, thus increasing the risk of poor  nutrition and the ability to adapt to a potentially powerful stressor.

Although proof is not possible, we have accumulated a lot of evidence that has enabled us to hypothesize that the vaccination acted as a nonspecific form of stress in people who were marginally thiamine deficient, but asymptomatic before receiving the vaccine. For the youngster who had not received the vaccine, but who had succumbed to POTS, poor nutrition alone, with or without genetic risk, had to be blamed. Genetics, stress and nutrition are visualized as the “three circles of health“.

The Medical Revolution

We are proposing that energy loss is the major cause of disease and that it results commonly from a less than ideal diet or dysfunctional mitochondria. Failing in the balanced need of the caloric content and the  necessary non-caloric vitamins and minerals for efficient oxidation, the result of poor diet is energy deficiency. There is considerable evidence that thiamine plays a vital part in both the production of chemical energy (ATP) and its conversion to electrical energy for bodily function. We have concluded, also from evidence, that genes may or may not usually cause disease on their own. Either nutrition or overwhelming stress may be variable factors that create genetic risk. The prevailing addiction to sugar creates a variable degree of thiamine deficiency by the catatorulin effect. We further hypothesize that a mild to moderate thiamine deficiency leads to a gradual decay in the efficiency of the critical enzyme(s), insufficiently supported by the cofactor(s). Attributing the easily reversible symptoms to other causes and allowing them to continue, leads to chronic disease. This may or may not respond to pharmacological doses of cofactor, used to resuscitate the associated enzyme(s).

We Need Your Help

More people than ever are reading Hormones Matter, a testament to the need for independent voices in health and medicine. We are not funded and accept limited advertising. Unlike many health sites, we don’t force you to purchase a subscription. We believe health information should be open to all. If you read Hormones Matter, like it, please help support it. Contribute now.

Yes, I would like to support Hormones Matter.

Image by Jonny Lindner from Pixabay.

This article was first published on July 1, 2019.    

Rest in peace Derrick Lonsdale, May 2024.